Dandruff or scalp irritation? Try BLOO.

  • 0 Votes
    3 Posts
    125 Views
    T
    @Lejeboca so the injured brains were loaded with EPA and DHA. Ray Peat argued in The Great Fish Oil Experiment that low levels of these oils usually get read as a deficiency, when "it is usually their presence, rather than their deficiency, that created the disposition for the disease." Does the paper say anything about how much fish those six guys ate? I'm wondering if it came from diet or if it just piles up in damaged tissue.
  • 1 Votes
    1 Posts
    47 Views
    No one has replied
  • 0 Votes
    1 Posts
    41 Views
    No one has replied
  • 0 Votes
    1 Posts
    80 Views
    No one has replied
  • 1 Votes
    3 Posts
    201 Views
    E
    I have been using structured water, and various forms of red light for about ten years now, and I was always so confused by the Peatsphere’s perspective that structured water was useless, (especially since my personal experience directly contradicted it). I get that Danny, Ray, and Georgie all said, “but stomach acid!” But this is such a limited perspective! First, it touches the lips, internal mouth, throat, (passes by the fricken thyroid!) before it hits the stomach. If this liquid is energized and has the ability to structure those things it comes in contact with, it’s clearly beneficial outside of ingestion. And this doesn’t even touch on topical applications, (soaking an elbow with tendinitis in a bowl of it for instance). Such an odd perspective from Ray, Georgie, and Danny, “no I’ve never tried it, but it can’t work, so meh…”
  • 0 Votes
    4 Posts
    166 Views
    LucHL
    @AlphaZance said: Stoichiometric Limitation: One molecule of Vitamin E quenches one peroxyl radical before needing to be recycled by Vitamin C or Glutathione. It protects the surrounding bis-allylic motifs as long as active Vitamin E levels are maintained. Hi, Thanks for the post. I've been searching for additonal info, trying to connect the dots. (8 pages docx for an article on my forum). Here is a no-conventional aspect: There is a bidirectional save effect between AA and tocos. Translation of an excerpt: Bidirectional recycling: Once Vitamin E is regenerated (recycled by ascorbic acid), its membrane anchoring allows it to act as a shield; this not only exerts a sparing effect on the nearby ascorbic acid but also enables a bidirectional exchange. The precise mechanism of this reciprocal support remains a complex biochemical challenge, yet the outcome is clear: the two molecules protect and sustain each other amidst the oxidative storm.
  • 0 Votes
    2 Posts
    105 Views
    LejebocaL
    @haidut said: ... it may very well be helpful for cancer too. The reason to use B3 in this study was explained, in part, by its prior use for skin cancer prevention: "In a phase III randomized, placebo-controlled trial by Chen et al, [8] oral nicotinamide administered at 500 mg BD for 12 months was safe and effective in reducing the incidence of nonmelanoma skin cancer and actinic keratoses in individuals who were at high risk. " [8] Chen AC, Martin AJ, Choy B, et al. A phase 3 randomised trial of nicotinamide for skin-cancer chemoprevention. N Engl J Med 2015; 373(17):1618–1626. doi: https://doi.org/10.1056/NEJMoa1506197
  • Vitamin B6 (monotherapy) may treat depression

    1
    1 Votes
    1 Posts
    76 Views
    No one has replied
  • 0 Votes
    2 Posts
    88 Views
    LejebocaL
    @haidut Interesting find -- thankss! Yet another reason to keep the glucose uptake high and to avoid metabolic stess. From this paper's concluding passages [bold-facing is mine]: "These results also have implications for therapeutic strategies that manipulate cyst(e)ine availability. Intracellular cysteine became toxic at concentrations of approximately 1–1.5 mM (Extended Data Fig. 4l), substantially above its normal systemic abundance. In fasting human plasma, free cysteine and cystine are present at approximately 10 µM and 80 µM, respectively, with total cyst(e)ine reaching ~250 µM (refs. 31,32). Thus, the toxic threshold is unlikely to be reached through bulk plasma exposure but may be approached in cells with unusually high cyst(e)ine uptake or impaired cysteine disposal. One such example would be cancers with constitutive NRF2 activation that accumulate cysteine beyond biosynthetic demand through upregulation of SLC7A11, promoting the formation of cysteine-derived conjugates that may serve as a detoxification route [33]. Cysteine or NAC has also been reported to induce cell death in glioblastoma and other cellular contexts, particularly during metabolic stress¹¹,³⁴. Our study suggests that, when this buffering capacity is exceeded, or under conditions of metabolic stress such as glucose limitation, excess cysteine becomes deleterious. Conversely, cystine supplementation can enhance tissue regeneration and stem-cell function in some settings.³⁵. Such findings are therefore likely to depend on the capacity of the receiving cells to metabolize or safely dispose of the resulting cysteine. Cysteine damages the mitochondrial electron transport chain via iron–sulfur protein loss, leading to cells relying more on glycolysis for ATP production and trying to uptake more glucose (Extended Data Fig. 4b). This would explain why glucose starvation is synthetically lethal with high cyst(e)ine as exemplified by disulfidptosis, although this death cannot be rescued by iron chelation [10]. Although this process shares features with ferroptosis, it occurs despite elevated GSH and suppressed lipid peroxidation, defining a distinct form of mitochondrial iron-dependent cell death (Extended Data Fig. 4m). Together, these results position thiol imbalance as a central metabolic vulnerability and underscore the importance of both limiting cysteine accumulation and promoting its safe disposal to maintain cellular homeostasis. "

  • 0 Votes
    1 Posts
    59 Views
    No one has replied
  • 0 Votes
    1 Posts
    45 Views
    No one has replied
  • 0 Votes
    1 Posts
    38 Views
    No one has replied
  • 0 Votes
    1 Posts
    45 Views
    No one has replied
  • 0 Votes
    1 Posts
    62 Views
    No one has replied
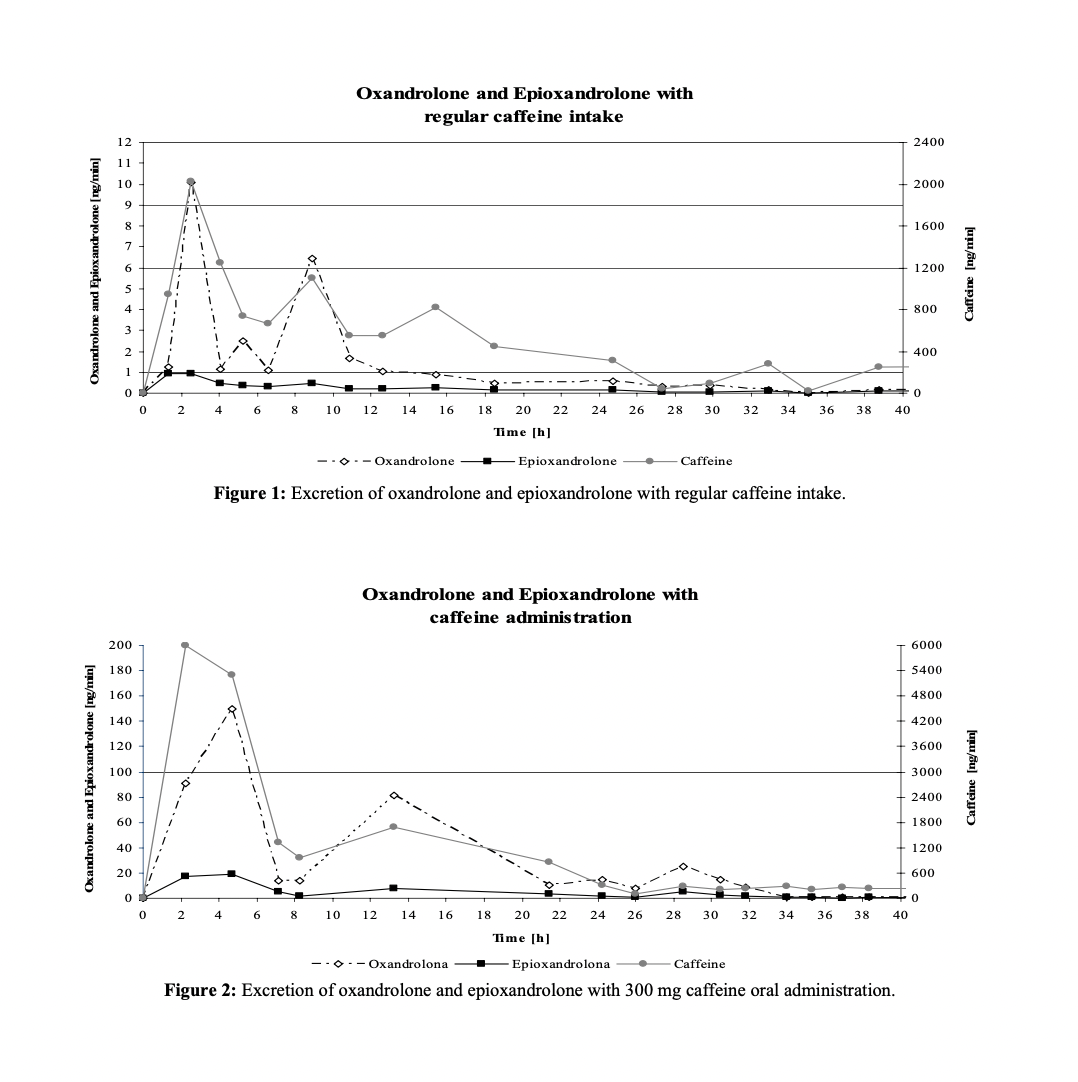
  • Anavar and Caffeine, revisited

    coffee steroids bodybuilding hormones
    5
    1
    0 Votes
    5 Posts
    2k Views
    chudlordC
    @jamezb46 is it not more likely that this is merely increased excretion rather than increased absorption?
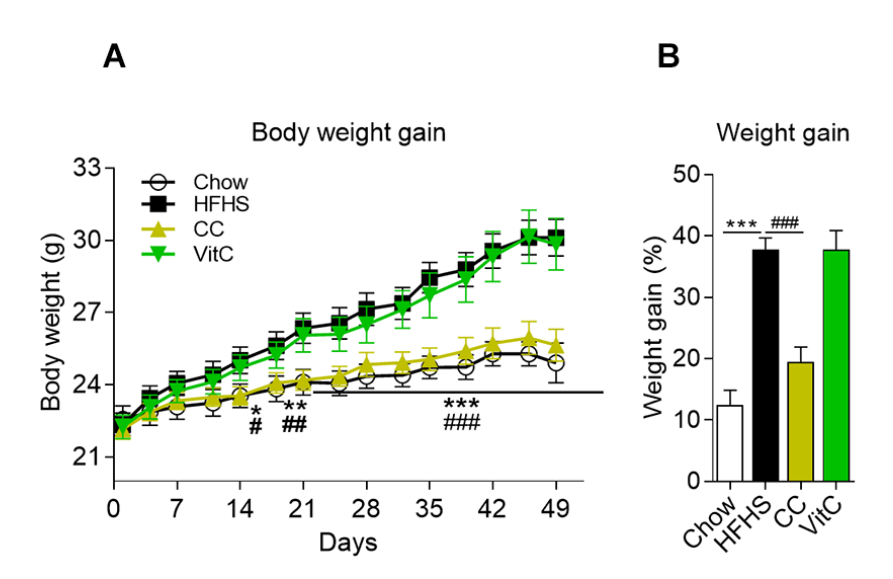
  • Camu Camu = pro-metabolic?

    camu-camu ucp-1 dio2 akkermansia turicibacter
    3
    2
    0 Votes
    3 Posts
    212 Views
    daposeD
    I got some camu camu powder today and put 1/4 tap in some OJ and the effects are nice. Calming energy. And seems to perhaps prevented this late afternoon histamine release I get sometimes. I live in one of the worst cities in the world for seasonal allergies. I will continue with the smaller 100mg doses.
  • 2 Votes
    128 Posts
    38k Views
    C
    @Mauritio said: @crumblingcookie any new insights ? Yes. Hesperitin seems good and yielding more energy throughout the day in a calm, non-exciting manner through its mitochondria-boosting MoA. Have been taking c. 500mg twice daily. I've been wondering, though, whether the second dose may already be too much (for me in my condition). Still curious about how hesperitin fares in healthier folks in comparison with hesperidin from bergamot extract. Naringin/GSE. Some drops on the tongue quickly made the tongue look rosier and fresher each time. Maybe a good thing before going out and french kissing. Disodium EDTA. Had started with 100mg, then went to 250mg, then 500mg and ultimately 750mg on an empty stomach once daily. Caveat: Really strong chelator of Ca in practice; soon my feet started aching all day as if I had been on a 10miles hike the day before. I suspect decalcification of the foot bones. It still lasted after stopping Na2-EDTA. Distinct improvements each time after supplementing calcium but tbh I can still feel it a month later. Nystatin. IMO 2.5M units (five tablets) four times daily is plenty and there's no use of doing any more like the 5M QID I did. The pharmacy tablets are probably fine. If there's no positive effect from 2-2.5M QID I suggest to look for a different cause. Beyond that, fluconazole for three weeks appears to be a reasonable diagnostic trial or probatory treatment wrt harbouring suspicions of a fungal infection which cannot (yet) be ascertained in other ways, as per Satish Rao MD's proceedings. Although when in suspicion of any extramucosal/extraintestinal fungal involvement I'd escalatate that to 400mg pd instead of a mere 100mg. On the plus side, I really seem to be quite free from any Candida and intestinal biofilm. On the downside, all miseries perdure and it's come to light to actually be Blastomyces disseminated to the brain and cerebrospinal fluid. With the utter dysfunctioning of GI mechanism sort of a last link in the chain of progressive systemic impairments; a final nail in the coffin by general immune exhaustion or centrally-mediated nervous deregulation (reminiscent of that 1930s study where they cut the CNS connection to the ENS). Ah, fun(!) times. What a curveball. Finally explains the headaches beyond all bearing and other things. Doing 700mg pd fluconazole rn while the public health services are passing the buck between factual denial and each other's possible responsibilities with my hopes and expectations in them being severely muted. Fluco is sadly the specifically worst effective azole: Far inferior to double- or triple-dose itraconazole, posaconazole or voriconazole and they are all reported as specifically fungistatic follow-up-treatments after an imperative initiation with i.v. liposomal Amphotericin B. No β-glucan targeting in Blastos because they synthesize α-glucan. On top, blasto yeasts have exceptionally high chitin content. No outer/secreted aspartyl proteases as targets either and no public research on antifungal synergy by inhibition of their internal/vacuolar AsPs. The clinical guidelines handed on the clinically related Cryptococcus btw about are piss-poor and in stark divergence with what's actually known.
  • Random, interesting studies

    412
    0 Votes
    412 Posts
    127k Views
    MauritioM
    @CrumblingCookie Oh yeah, youre right. Thanks for pointing that out. I still find it interesting. Antrodia camphorata The fungus I mentioned, is available as a supplement .
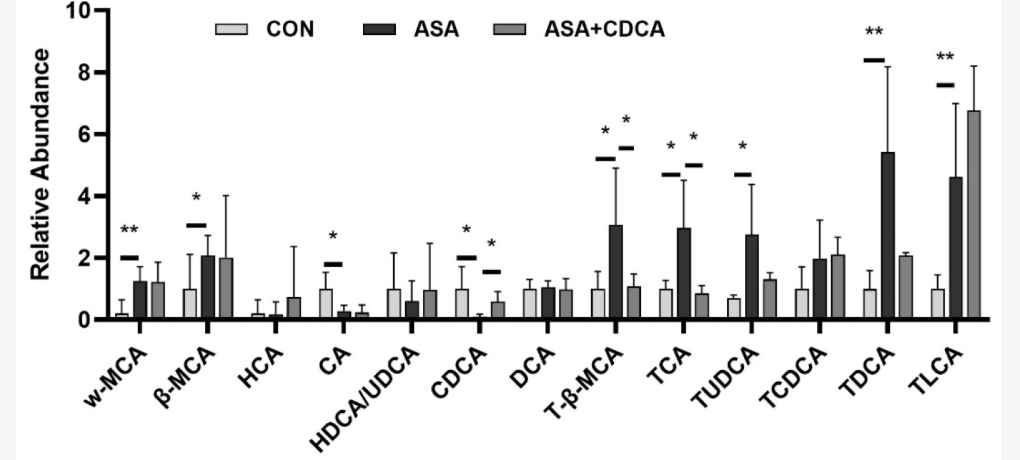
  • Aspirin causes intestinal damage?

    20
    1
    1 Votes
    20 Posts
    6k Views
    B
    Pure aspirin powder, especially when dissolved cleanly in warm water or a metabolic substrate like orange juice is absorbed primarily in the upper GI tract, ensuring it never reaches the small intestine as a concentrated solid. The aspirin in this study and the ones like it utilize enteric coated aspirin. Known as Bayaspirin the enteric coating utilizes methacrylic acid copolymer, often branded as Eudragit, along with other excipients like Titanium Dioxide, plasticizers, and synthetic dyes. Pretty nasty, pretty irritating especially a concentrated, focused amount of it on the intestinal lining. This kinda crap reminds of the 1918 or so studies where enormous amounts of aspirin were used and it was then said aspirin was terrible for the body.
  • 0 Votes
    3 Posts
    284 Views
    LejebocaL
    @pondfountain chronic caffeine consumption negates the Ach-increasing effects of caffeine. Chronic caffeine treatment reduces caffeine but not adenosine effects on cortical acetylcholine release The results indicate that prolonged consumption of high doses of caffeine causes changes in the responsiveness of cholinergic neurons to caffeine. The change is not shared by adenosine, through whose recognition sites caffeine is believed to act. It is therefore possible that the adaptive changes following repeated caffeine administration involve either only the coupler-transducer mechanism activated by the antagonist, or effects unrelated to receptors.